




Treating OCD with TMS - the evidence
Can obsessive compulsive disorder be treated with transcranial magnetic stimulation? Transcranial magnetic stimulation can help to reduce the symptoms and behaviours of obsessive compulsive disorder (OCD).
What are the NICE guidelines for treating OCD?
At Smart TMS we recommend that every patient with OCD should follow the NICE treatment guidelines. Psychological treatment should be provided first and this should include CBT with exposure and response prevention (ERP), administered by an experienced therapist. Patients with OCD who are resistant to psychological treatment alone should be offered treatment with an SSRI drug (Fluvoxamine, Paroxetine, Sertraline or Citalopram) combined with CBT/ERP. If there has not been an adequate response to a standard dose of an SSRI, then an increased dose should be considered. Clomipramine (a tricyclic antidepressant) should be considered after an adequate trial of at least one SSRI has been ineffective.
If this is not effective a number of other options can be prescribed by a Consultant Psychiatrist. This might include adding an antipsychotic drug to an SSRI or to Clomipramine or combining Clomipramine with Citalopram. If there has not been an adequate response to the standard dose of Clomipramine, an increased dose should be considered.
Somewhere in the region of 40% of patients with OCD are resistant to the above treatment.
How does Transcranial Magnetic Stimulation work?
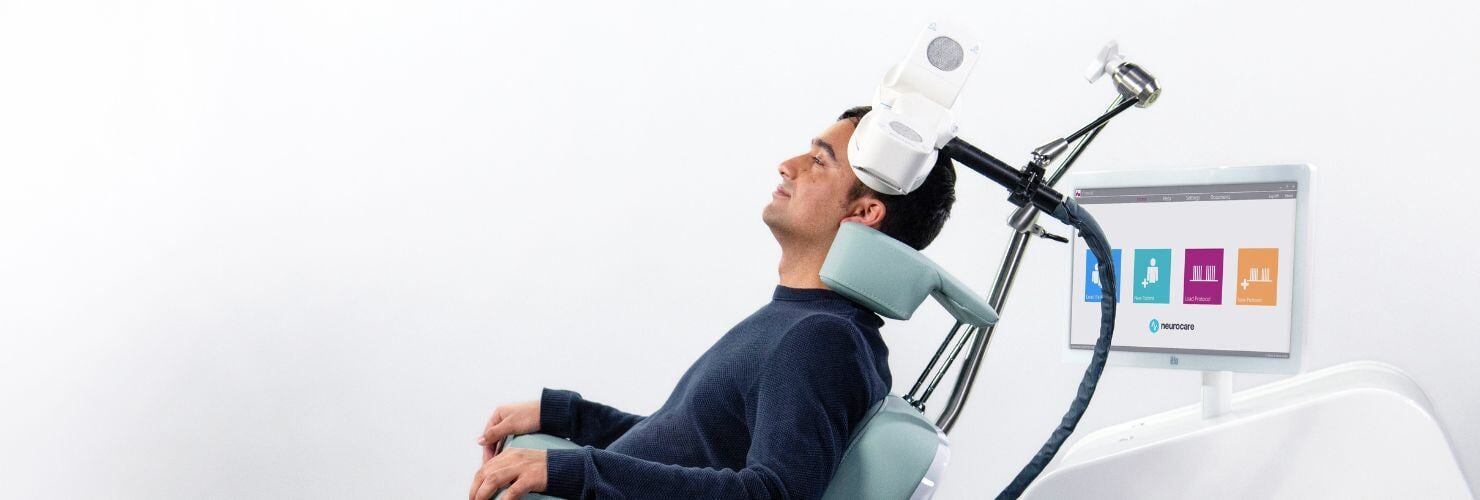
TMS is a pulsating magnetic field which stimulates brain cells and can change the excitability of these cells in the cortex of the brain. Low frequency TMS used in the treatment of OCD decreases cortical excitability and it is not associated with any serious side effects. A minority of patients may experience a transient headache or some local and transient discomfort over the treatment site.
What is the evidence for the treatment of OCD with TMS?
A meta-analysis by Fitzsimmons et al. (2022) examined 21 studies involving 662 patients with a diagnosis of OCD. rTMS significantly reduced OCD symptoms compared to sham treatment (effect size = –0.50, p < .001). The most effective stimulation sites were the dorsolateral prefrontal cortex and pre-supplementary motor area. A meta-analysis by Joseph et al. (2025) examined 7 studies involving 179 patients with OCD. Accelerated TMS (aTMS) significantly reduced OCD symptoms compared to sham (effect size = 0.63, p = 0.01) and patients were about four times more likely to respond (OR = 4.28, p = 0.02). aTMS also improved depressive symptoms (effect size = 0.52, p = 0.005), while adverse effects such as mild headache were more common (OR = 5.16, p = 0.006) dropout rates were similar. These findings support rTMS and aTMS as a rapid, safe, and effective option for OCD.
What are the treatment results at Smart TMS?
At Smart TMS, we analysed 112 patients who received treatment for OCD. Approximately 20% of patients experienced at least a 35% reduction in their symptoms, and 18% of patients entered remission based on Y-BOCS scores. These results reflect our commitment to delivering evidence-based treatment for individuals with refractory OCD.
Conclusions and recommendations:
OCD is a disabling condition that may not respond to standard therapies. At Smart TMS, we recommend beginning with NICE-approved treatments. However, for patients who do not improve with these approaches, TMS offers a non-invasive, evidence-supported alternative. We encourage patients to discuss this option with a qualified clinician when conventional treatments have been unsuccessful

Dr Leigh A Neal MB BCh FRCPsych MRCGP MD
Consultant in Psychiatry and Neuromodulation
Medical Director: Smart TMS





